本文属于主题馆「牙医」 → ← 回正文:牙周病与牙龈健康全指南:从牙龈炎到牙周炎的分期、治疗光谱与全身健康关联
牙周病与牙龈健康全指南:从牙龈炎到牙周炎的分期、治疗光谱与全身健康关联|證據鏈
本頁是〈牙周病与牙龈健康全指南:从牙龈炎到牙周炎的分期、治疗光谱与全身健康关联〉的事實單元帳:每一條主張對應的來源、證據等級、地域與期間、原文引句與限制,逐條攤開。
###事实(事实单元帐)
- F1|牙周健康被定义为临床上侦测不到发炎;牙龈健康与牙龈炎的个案定义主要建立在探测后是否出血。|来源 S1|confidence=high|basis=clinical_guideline(2017 世界工作坊 workgroup 1 共识报告)|geo: universal|period=2018 刊出|caveat:为定义与个案界定,非疗效宣称;临床与流行病学两种用途的个案定义另有区分。
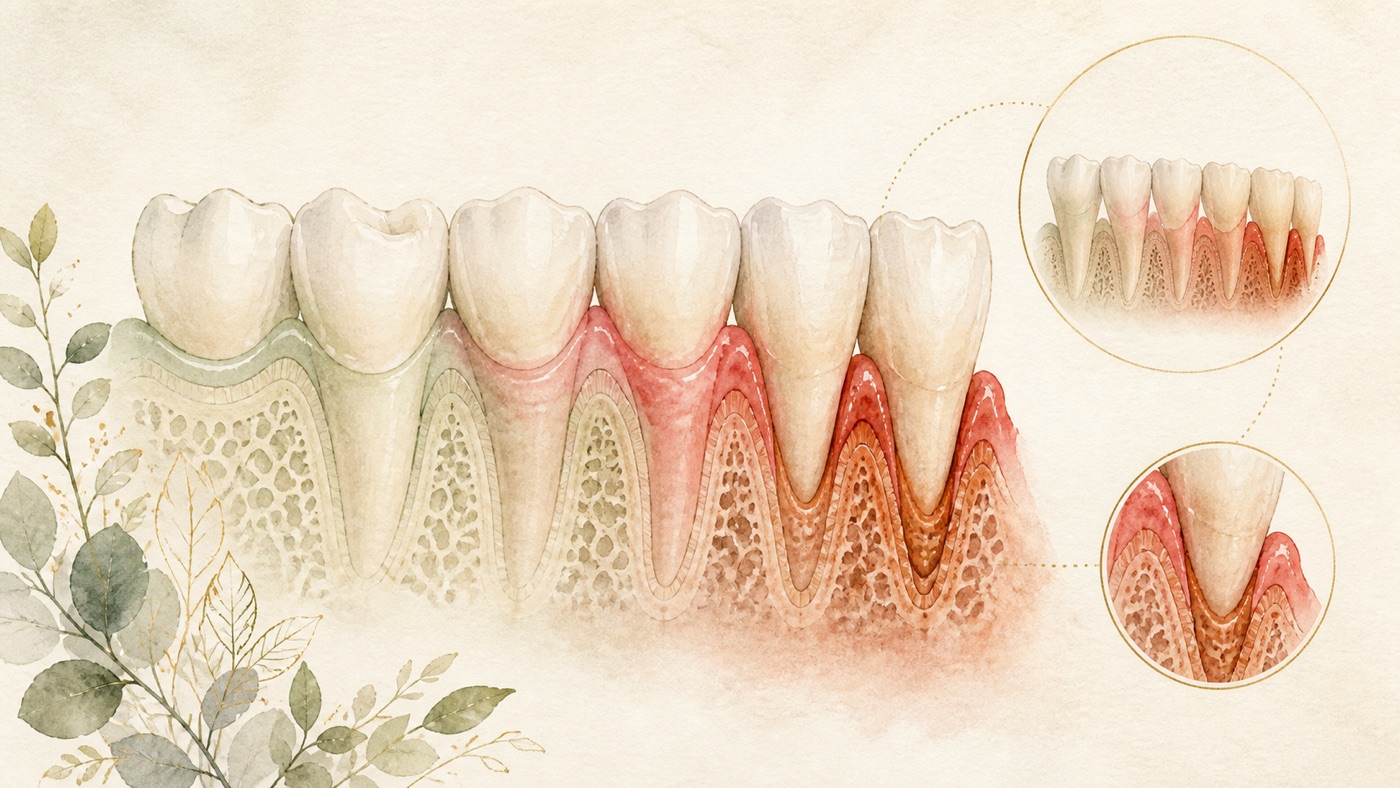
- F2|牙菌斑相关牙龈炎是可回复的发炎状况;在易感个体,牙龈炎可能进展为牙周炎并造成牙齿软组织与骨性支持的丧失。|来源 S3|confidence=high|basis=peer_reviewed(Cochrane 系统综述之背景陈述)|geo: universal|period=2017 刊出(检索至 2016-09)|caveat:「可能进展」为条件性陈述,非所有牙龈炎皆会进展。
- F3|牙周炎被描述为普遍且不可回复的发炎状况。|来源 S4|confidence=high|basis=clinical_guideline(第 11 届欧洲牙周病学研讨会工作小组共识报告)|geo: universal|period=2015 刊出|caveat:属疾病性质之描述;不可回复指已丧失的附连与骨支持,不等于无法控制。本来源并未写出「治疗目标是控制与维持」,故本文已将该推论改标为本站解读(见「四个状态」一节与 F28),不挂于本条。同一来源另写有「牙周炎可预防、治疗能降低失牙率并改善生活质量」一句,该句已独立立帐为 F29 并写入正文(60 字答案、第一节、FAQ 第 2 题),以免本文只单向呈现「不可回复」而漏掉同一段的正向结论。
- F4|牙龈健康可在治疗牙龈炎与牙周炎后恢复;但已治疗、目前牙龈健康的牙周炎病人仍处于复发之较高风险,须密切监测。临床牙龈健康可存在于完整牙周组织,也可存在于已减少的牙周组织(例如有牙龈萎缩者、牙冠增长术后者,或有牙周炎病史而目前稳定者)。|来源 S1|confidence=high|basis=clinical_guideline|geo: universal|period=2018 刊出|caveat:「密切监测」之频率未于该共识中量化,个别由临床决定。
- F5|牙龈疾病分两大类:非牙菌斑生物膜诱发之牙龈疾病(多种非牙菌斑造成之状况,去除牙菌斑后通常不会消退,可能为全身状况之表现或局限于口腔)与牙菌斑诱发之牙龈炎。|来源 S1|confidence=high|basis=clinical_guideline|geo: universal|period=2018 刊出|caveat:分类陈述,非诊断指引;个别病灶归类须临床判定。
- F6|非菌斑诱发性牙龈病灶系统综述(筛选 6,111 篇、纳入 461 篇):整体证据质量中等至极低;潜在恶性与恶性牙龈病灶需审慎评估并以切片取得诊断,之后多以外科方式处理;处置常需多专科照护,并常需转诊医科或口腔黏膜病专科。|span:「Over a total of 6111 articles initially identified, 461 met inclusion criteria」|来源 S14|confidence=high|basis=peer_reviewed(系统综述,Part 2)|geo: universal|period=2026 线上刊出|caveat:纳入设计自病例报告至随机试验,异质性高;本文仅引用其分流与转诊层级之结论,不引用个别病灶之处置细节。
- F7|分期 Stage I 至 IV 依严重度(以牙根长度为参照之牙周破坏、与牙周炎相关之失牙)、处置复杂度(囊袋深度、牙槽骨内缺损、根分叉侵犯、牙齿过度动摇、咀嚼功能障碍)界定,并另以局限型或广泛型描述其范围。|来源 S2|confidence=high|basis=clinical_guideline(2017 世界工作坊个案定义框架)|geo: universal|period=2018 刊出(原文另有 2018 年勘误)|caveat:为个案定义框架,实际归期须由临床检查与影像判定。
- F8|分级 Grade A 至 C 以直接或间接之进展速率证据估计(慢速、中速、快速三类);风险因子分析被用作分级之修正因子。|来源 S2|confidence=high|basis=clinical_guideline|geo: universal|period=2018 刊出|caveat:同上;风险因子之个别权重未于摘要层级量化。
- F9|Stage IV 与 Stage III 共有严重度与复杂度特征,但另含牙齿与牙周附连丧失所致之解剖与功能后遗症(牙齿外飘与移位、咬合塌陷等),须于主动牙周治疗完成后追加介入。|来源 S7|confidence=high|basis=clinical_guideline(EFP S3 等级临床实务指引)|geo: universal|period=2022 刊出|caveat:指引全文为期刊付费内容,本条仅依 PubMed 摘要逐字引用,不扩写为全文内容。
- F10|EFP 针对 Stage I 至 III 牙周炎之 S3 等级临床实务指引,由 15 篇特别委制之系统综述、证据质量与强度评估及 GRADE 流程产出,采预先设定之阶梯式治疗路径;原文为「a pre-established stepwise approach to therapy that, depending on the disease stage, should be incremental, each including different interventions」——升阶条件写的是疾病分期(disease stage),不是前一阶的治疗反应。|span:「15 specifically commissioned systematic reviews」/「a pre-established stepwise approach to therapy that, depending on the disease stage, should be incremental, each including different interventions」|来源 S6|confidence=high|basis=clinical_guideline|geo: universal|period=2020 刊出(另有 2021 年勘误)|caveat:指引全文为期刊付费内容,本条仅依 PubMed 摘要逐字引用;适用范围限 Stage I 至 III。本条为 2026-08-06 修正回合新增之界线:本文原有三处(费用拆法手术段、FAQ「牙周病一定要开刀吗」、阶梯表白话栏)把升阶条件写成「前面阶段的反应」并挂 11,该条件变数未见于任一来源摘要,已全部改回「疾病分期」,个别病人之进入与否改标 F28。
- F11|该指引达成共识之建议涵盖四类介入:(a) 行为改变、龈上生物膜、牙龈发炎与风险因子控制;(b) 龈上与龈下器械清创,加上或不加上辅助疗法;(c) 各类牙周手术介入;(d) 支持性牙周治疗以延续疗效于时间之上。|来源 S6|confidence=high|basis=clinical_guideline|geo: universal|period=2020 刊出|caveat:(a)–(d) 为介入类别之列举,摘要层级未载各项建议之强度等级;本文对「手术排序在后」之解读属阶梯式设计之直接推论,不等于任何个案之处置顺序。本条不得被用来支撑「以前一阶之治疗反应作为升阶触发条件」之宣称(该条件变数见 F10 之界线说明)。
- F12|Stage IV 指引之建议介入包含矫正性牙齿移动、牙齿夹板固定、咬合调整、牙齿或种植体支持之固定或活动假牙,以及支持性牙周治疗;治疗计划前须完成明确而完整之诊断与病例评估、取得相关病人信息,并于治疗期间与治疗后频繁再评估。|来源 S7|confidence=high|basis=clinical_guideline|geo: universal|period=2022 刊出|caveat:同 F9;牙周部分之治疗仍依 Stage I 至 III 指引执行。
- F13|共识报告记录:牙间刷为邻接面牙菌斑清除之建议器械(原文 device of choice);牙线不被建议用于牙龈与牙周健康、且牙间刷无法无创通过之部位以外的情境。|来源 S4|confidence=high|basis=clinical_guideline|geo: universal|period=2015 刊出|caveat:本文依内容合规要求不使用比较性与极端措辞,原文语汇保留于 span;个别器械之适用尺寸与部位须由牙医师或牙体卫生人员指导。
- F14|局部或全身性抗发炎药剂用于牙龈炎之处置,没有稳固的证据基础。|来源 S4|confidence=high|basis=clinical_guideline|geo: universal|period=2015 刊出|caveat:为证据缺口陈述,非安全性结论;本文不涉任何药品之使用指示。
- F15|儿童与青少年(无已知全身疾病)系统综述(纳入 269 篇研究):牙菌斑诱发性牙龈炎常见(52%)并与较差之口腔健康相关生活质量有关;有效处置应结合监督式刷牙与含氟牙膏及学校或照顾者为基础之口腔卫生教育,氯己定之辅助使用在特定临床情境可能提供额外助益。|span:「Ultimately, 269 studies, all restricted to biofilm-induced gingivitis, were included」/「Dental biofilm-induced gingivitis was common (52%) and associated with poorer OHRQoL」/「effective management of gingivitis in children should combine supervised toothbrushing with a fluoridated toothpaste and school- or caregiver-based oral health education」|来源 S8|confidence=moderate|basis=peer_reviewed(系统综述)|geo: universal|period=2026 刊出(检索至 2025-01)|caveat:人群限儿童与青少年且无已知全身疾病者,不可外推至成人;作者自述诊断标准与研究质量异质性高。
- F16|Cochrane 系统综述(51 篇研究、5,345 位受试者)评估氯己定漱口水作为机械性口腔清洁之辅助。作者结论记录:在平均为轻度牙龈发炎者(0 至 3 分牙龈指数平均 1 分)观察到之牙龈炎下降「未被认为具有临床意义」;对平均牙龈指数 1.1 至 3(中度或重度发炎)者,证据不足以判定其减少牙龈炎之幅度。该回顾同时记录外源性牙齿染色之大幅增加,以及味觉干扰或改变、口腔黏膜疼痛刺激轻微脱屑与溃疡糜烂、一般性或舌头灼热感等不良反应。|span:「We included 51 studies that analysed a total of 5345 participants」|来源 S3|confidence=high|basis=peer_reviewed(Cochrane 系统综述)|geo: universal|period=2017 刊出(检索至 2016-09)|caveat:51 篇纳入研究中 50 篇为高偏差风险;本 Pillar 仍刻意不引用其效应量数字与浓度比较(该题之效应量解读属 KM-DENTAL-06 正典卡范围),但作者对临床意义之结论句属平衡陈述之必要成分,不得只引代价侧,故予引用;「未达临床意义」系针对轻度发炎人群之牙龈指数,不可外推为「无效」或「不必用」,亦不可外推至中重度人群;本文不指名任何产品、不提供浓度与使用频率。
- F17|CPC 与氯己定漱口水之直接比较,已有系统综述与荟萃分析(424 篇筛出 14 篇全文、18 组比较)就牙菌斑与牙龈炎指标进行。|span:「The search resulted in 424 unique papers, from which 14 full-text papers providing 18 comparisons were selected」|来源 S9|confidence=moderate|basis=peer_reviewed(系统综述+荟萃分析,GRADE 评级)|geo: universal|period=2025 刊出|caveat:本 Pillar 仅陈述该比较之存在,刻意不引用其方向与效应量(「该选哪一种成分」属 KM-DENTAL-06 正典卡之任务,Pillar 层不得代答);纳入研究之偏差风险分布为低至高;作者揭露部分纳入研究有业界资助。
- F18|Er:YAG 激光作为非手术牙周治疗辅助之 umbrella review(472 篇筛出、纳入 4 篇系统综述)结论:虽观察到弱效证据,临床效益仍然不足。|span:「A total of 472 studies were initially identified. After removing the duplicates and screening, a total of four studies were selected for the current overview」|来源 S13|confidence=moderate|basis=peer_reviewed(umbrella review,AMSTAR 2 评估)|geo: universal|period=2024 刊出(检索 2011–2023)|caveat:纳入之 4 篇系统综述质量分别为高、中、低与极低;本条仅涵盖 Er:YAG,不可外推至其他激光种类与波长;其他波长或机型是否有对应证据,需另行检索该类激光之文献,本文未做此检索。
- F19|多发性牙龈萎缩之根面覆盖手术,文献同时以专业端美学评估与病人自评结果(PROMs)两套指标衡量。|来源 S11|confidence=high|basis=peer_reviewed(系统综述+荟萃分析)|geo: universal|period=2025 刊出(检索至 2024-05)|caveat:本 Pillar 仅引用其结果指标架构,刻意不引用其覆盖率与满意度数字(属 KM-DENTAL-14/27 正典卡范围)。
- F20|自体结缔组织移植与异种软组织替代物之直接比较,已有系统综述与荟萃分析(16 篇 RCT、632 位病人、1,878 处萎缩)就多发性牙龈萎缩之治疗进行。|span:「Sixteen RCTs (632 patients, 1878 recessions) were included」|来源 S10|confidence=moderate|basis=peer_reviewed(系统综述+荟萃分析,RoB 2)|geo: universal|period=2026 刊出(检索至 2025-10)|caveat:本 Pillar 仅陈述该比较之存在,刻意不引用其方向与效应量(「移植物来源该选哪一种」属 KM-DENTAL-14 正典卡之任务,Pillar 层不得代答;此纪律与 F21 一致);人群限多发性牙龈萎缩;作者自述需更大样本与标准化结果之试验以验证长期稳定性。
- F21|美学牙冠增长术之开放翻瓣与微创无翻瓣两种术式,已有随机试验之系统综述与荟萃分析进行比较(纳入 5 篇 RCT、180 位病人)。|来源 S12|confidence=moderate|basis=peer_reviewed(系统综述+荟萃分析)|geo: universal|period=2025 刊出|caveat:本 Pillar 仅陈述该比较之存在,刻意不引用其方向与效应量(属 KM-DENTAL-17 正典卡范围);原研究人群限过度牙龈显露(EGD)之美学适应证,不涵盖修复性/生物宽度等其他适应证,此界线已写入正文与下链表;本条不含牙冠增长术之解剖定义(该定义未见于本来源摘要,本文已删除该无源句)。
- F22|全球疾病负担系统综述与统合回归(72 篇研究、37 国、291,170 位 15 岁以上受试者):重度牙周炎为全球第六常见之状况;1990 至 2010 年全球年龄标准化患病率维持在 11.2%;患病率随年龄上升,发生率高峰约在 38 岁。|span:「72 studies, including 291,170 individuals aged 15 yr or older in 37 countries」/「the global age-standardized prevalence of SP was static at 11.2%」/「SP was the sixth-most prevalent condition in the world」/「peak in incidence at around 38 yr of age」|来源 S5|confidence=high|basis=peer_reviewed(系统综述+统合回归,GBD 2010 模型)|geo: universal|period=1990–2010(2014 刊出)|caveat:资料期间止于 2010,非现况估计;「重度牙周炎」之个案定义早于 2017 年分期分级系统,与现行分期分级不可直接对应。2026-08-06 检索另见更新之全球负担文献,本文未逐一验证故未采用,因此本条仅代表 1990–2010 期间之估计;「第六常见」此一排序与 11.2% 同属该期间之估计,正文已加注年份界线。S16 的 11.2% 系转引本条同一份 GBD 2010 估计,两者同源、非彼此独立之佐证,并陈仅为呈现该估计在学会共识层级被沿用,不相加亦不视为重复计算。
- F23|EFP 与世界心脏联盟联合工作坊共识报告:重度牙周炎影响全球 11.2% 人口,为第六常见之人类疾病;该报告更新重度牙周炎与心血管疾病间流行病学关联之证据、机制连结,以及牙周治疗对心血管结果与替代指标之影响,并针对接受抗血栓治疗病人之牙周治疗风险与并发症提出说明与建议。|span:「being severe periodontitis, affecting 11.2% of the world's population, the sixth most common human disease」|来源 S16|confidence=high|basis=clinical_guideline(国际学会联合共识报告)|geo: universal|period=2020 刊出|caveat:原文措辞为「关联(associations)」,非因果宣称;11.2% 系转引 F22 之同一份 GBD 2010 估计,两条同源、不得被读成独立佐证,本文并陈而不相加,正文已明写此点。
- F24|EFP 与国际糖尿病联盟联合工作坊共识报告:有强力证据显示牙周炎患者出现血糖异常与胰岛素抵抗之风险升高;糖尿病人群之队列研究显示合并牙周炎者糖化血红蛋白较高,但第 1 型糖尿病资料不足;牙周炎与新发第 2 型糖尿病风险增加有关;牙周治疗于糖尿病人安全且有效,并与治疗后 3 个月糖化血红蛋白下降 0.27% 至 0.48% 有关,惟较长期随访之研究结论不一致。|span:「Periodontal therapy is safe and effective in people with diabetes, and it is associated with reductions in HbA1C of 0.27-0.48% after 3 months, although studies involving longer-term follow-up are inconclusive」|来源 S15|confidence=high|basis=clinical_guideline(国际学会联合共识报告与指引)|geo: universal|period=2018 刊出|caveat:0.27%–0.48% 为 3 个月之群体估计,不可用于推估个人血糖改善幅度;长期效果原文自述结论不一致。
- F25|Cochrane 系统综述(更新版):该回顾记录,来自一项成人试验之高确定性证据显示,4 年随访中风险导向复诊与 6 个月复诊在有牙龈出血之部位比例上几乎没有差异(平均差 0.78%,95% CI −1.17% 至 2.73%,1,472 位受试者)。|span:「there is little to no difference between risk-based and 6-month recall intervals in the number of tooth surfaces with any caries, gingival bleeding and oral-health-related quality of life over a 4-year period (high-certainty evidence)」/「proportion of sites with gingival bleeding (MD 0.78%, 95% CI -1.17% to 2.73%; 1472 participants)」/「One study was conducted in a public dental service clinic in Norway and involved participants under 20 years of age who were regular attenders at dental appointments. It compared 12-month with 24-month recall intervals」|来源 S17|confidence=high|basis=peer_reviewed(Cochrane 系统综述,GRADE)|geo: universal|period=2020 刊出(检索至 2020-01)|caveat:人群为基层牙科之规律就诊成人、比较的是一般定期口腔检查间隔,不涵盖牙周炎病人之支持性牙周治疗复诊间隔;纳入研究仅 2 篇、共 1,736 位受试者,其中成人段仅 1 篇(英国一般牙科诊所,原文为 from one trial of adults),另 1 篇为挪威 20 岁以下人群、比较 12 与 24 个月间隔——证据基底为单一试验,不得被读成「多篇回顾的合并发现」;本文未检索支持性牙周治疗复诊间隔本身之文献,故对该情境不作任何全称陈述。
- F26[结构性整理]|「诊断评估/非手术/手术/维护」四段费用拆法,为本站依 S6 阶梯结构所做之阅读框架,非事实宣称、非任何机构之收费分类、不含任何金额。|confidence=n/a|basis=editorial|geo: universal|caveat:不得标为待验;跨制度之给付与收费规定一律不在本文范围。
- F27[编务声明]|本文之卫教定位、地域声明、下链规则(69 题伫列之具体问题仅一句摘述加内部引用)与挂载区留空之决定。|confidence=n/a|basis=editorial|geo: universal|caveat:编务声明,非医学事实宣称;医疗广告合规之法域判定依发布地规定,由发布端于上线前确认。
- F28[编务建议与本站解读]|本文中明标为「本站建议」或「本站解读」之句,逐条列举:①把牙周处置理解为长期控制与维护、而非回到治疗前组织状态(依 F3 与 F11 之并读);②非菌斑诱发性病灶特征出现时回头请牙医师重新评估诊断,而非继续加强清洁(第二节、第八节各一处);③判断激光证据前先向牙医师确认机型与波长,再对照该类激光之文献;④抗菌漱口产品之使用与否、浓度与期间由牙医师依诊断决定;⑤用药史于治疗前主动告知牙医师;⑥把 F11 四类介入读成先后顺序,系依「阶梯式、逐步加叠」之设计所做之解读(指引摘要未逐字写明顺序);⑦本文将手术分成三条线,系本文之地图分法,非任何来源之分类;⑧「本文能引用到的高确定性证据落在相邻情境」系本文检索范围之自陈,非对全球文献之全称否定。|confidence=n/a|basis=editorial|geo: universal|caveat:上列各句皆为编务与安全导向之建议或解读,不是任一来源的临床指示、诊断标准或治疗处方;个别情况一律由牙医师判定。设立本条之目的,是避免无来源之临床行动句以 [Fn] 形式伪装成有来源。
- F29|牙周炎为可预防;治疗可降低失牙率并改善生活质量。|来源 S4|confidence=high|basis=clinical_guideline(第 11 届欧洲牙周病学研讨会工作小组共识报告,PMID 25639826)|geo: universal|period=2015 刊出|span:「preventable and treatment leads to reduced rates of tooth loss and improved quality of life」(2026-08-06 以 E-utilities efetch 实测取回、逐字对得上)|caveat:与 F3「不可回复」为同一份共识报告同段之两面,两者须并读——「不可回复」指已丧失之附连与骨支持,「可预防、治疗有益」指疾病进程可控;引用时不得只取其中一面。属人群层级之结论,非个别预后保证。
- F30|在牙龈炎病人,建议每日一次邻接面清洁,且该人群辅助使用化学性牙菌斑控制制剂具有优势。|来源 S4|confidence=high|basis=clinical_guideline(同 F29,PMID 25639826)|geo: universal|period=2015 刊出|span:「In patients with gingivitis once daily inter-dental cleaning is recommended and the adjunctive use of chemical plaque control agents offers advantages in this group」(2026-08-06 实测取回、逐字对得上)|caveat:人群限定为牙龈炎病人,不得外推至牙周健康者或牙周炎病人(同一份共识对其他人群之化学辅助评价不同);本文不指定任何产品、浓度或使用期间,该等决定由牙医师依诊断为之。
来源清单(17 条,取用日期一律 2026-08-06)
逐字 span 一律取自 PubMed E-utilities(efetch)回传之摘要正文;空白字元已正规化(部分原文含 non-breaking space 与 thin space),其余字元与原文完全一致。指引与共识报告之期刊全文多为付费内容、本机未能取回,因此所有 span 仅取自 PubMed 摘要,正文不扩写为全文内容。
S1|Chapple ILC, Mealey BL, Van Dyke TE, et al. Periodontal health and gingival diseases and conditions on an intact and a reduced periodontium: Consensus report of workgroup 1 of the 2017 World Workshop on the Classification of Periodontal and Peri-Implant Diseases and Conditions. J Clin Periodontol. 2018;45 Suppl 20:S68-S77. PMID 29926499. (取用 2026-08-06,HTTP 200) span:「Periodontal health is defined by absence of clinically detectable inflammation」/「case definitions are primarily predicated on presence or absence of bleeding on probing」/「the treated and stable periodontitis patient with current gingival health remains at increased risk of recurrent periodontitis, and accordingly, must be closely monitored」/「usually do not resolve following plaque removal」
S2|Tonetti MS, Greenwell H, Kornman KS. Staging and grading of periodontitis: Framework and proposal of a new classification and case definition. J Periodontol. 2018;89 Suppl 1:S159-S172. PMID 29926952. (取用 2026-08-06,HTTP 200) span:「Stage I to IV of periodontitis is defined based on severity」/「Grade of periodontitis is estimated with direct or indirect evidence of progression rate in three categories: slow, moderate and rapid progression (Grade A-C)」/「Risk factor analysis is used as grade modifier」
S3|James P, Worthington HV, Parnell C, et al. Chlorhexidine mouthrinse as an adjunctive treatment for gingival health. Cochrane Database Syst Rev. 2017;3(3):CD008676. PMID 28362061. (取用 2026-08-06,HTTP 200) span:「Dental plaque associated gingivitis is a reversible inflammatory condition」/「In susceptible individuals, gingivitis may lead to periodontitis and loss of the soft tissue and bony support for the tooth」/「There is high-quality evidence from studies that reported the Löe and Silness Gingival Index of a reduction in gingivitis in individuals with mild gingival inflammation on average (mean score of 1 on the 0 to 3 GI scale) that was not considered to be clinically relevant」/「There is insufficient evidence to determine the reduction in gingivitis associated with chlorhexidine mouthrinse use in individuals with mean GI scores of 1.1 to 3 indicating moderate or severe levels of gingival inflammation」/「There was a large increase in extrinsic tooth staining」/「taste disturbance/alteration (reported in 11 studies)」
S4|Chapple IL, Van der Weijden F, Doerfer C, et al. Primary prevention of periodontitis: managing gingivitis. J Clin Periodontol. 2015;42 Suppl 16:S71-S76. PMID 25639826. (取用 2026-08-06,HTTP 200) span:「Periodontitis is a ubiquitous and irreversible inflammatory condition」/「Periodontitis is preventable and treatment leads to reduced rates of tooth loss and improved quality of life」/「IDBs are the device of choice for interproximal plaque removal」/「Use of local or systemic anti-inflammatory agents in the management of gingivitis has no robust evidence base」
S5|Kassebaum NJ, Bernabé E, Dahiya M, et al. Global burden of severe periodontitis in 1990-2010: a systematic review and meta-regression. J Dent Res. 2014;93(11):1045-1053. PMID 25261053. (取用 2026-08-06,HTTP 200) span:「72 studies, including 291,170 individuals aged 15 yr or older in 37 countries」/「SP was the sixth-most prevalent condition in the world」/「the global age-standardized prevalence of SP was static at 11.2%」/「peak in incidence at around 38 yr of age」
S6|Sanz M, Herrera D, Kebschull M, et al. Treatment of stage I-III periodontitis—The EFP S3 level clinical practice guideline. J Clin Periodontol. 2020;47 Suppl 22:4-60. PMID 32383274. (取用 2026-08-06,HTTP 200)※ 锚定档来源 #06 span:「15 specifically commissioned systematic reviews」/「pre-established stepwise approach to therapy」/「(a) behavioural changes, supragingival biofilm, gingival inflammation and risk factor control; (b) supra- and sub-gingival instrumentation, with and without adjunctive therapies; (c) different types of periodontal surgical interventions; and (d) the necessary supportive periodontal care to extend benefits over time」
S7|Herrera D, Sanz M, Kebschull M, et al. Treatment of stage IV periodontitis: The EFP S3 level clinical practice guideline. J Clin Periodontol. 2022;49 Suppl 24:4-71. PMID 35688447. (取用 2026-08-06,HTTP 200) span:「anatomical and functional sequelae of tooth and periodontal attachment loss (tooth flaring and drifting, bite collapse, etc.), which require additional interventions following completion of active periodontal therapy」/「orthodontic tooth movement, tooth splinting, occlusal adjustment, tooth- or implant-supported fixed or removable dental prostheses and supportive periodontal care」/「it is critically important to undertake a definitive and comprehensive diagnosis and case evaluation」
S8|Tsilingaridis G, Tewari N, Seremidi K, Papaioannou W, López R. Dental Biofilm-Induced Gingivitis in Children and Adolescents Without Known Systemic Involvement: A Systematic Review. J Clin Periodontol. 2026;53(7):1226-1252. PMID 41905896. (取用 2026-08-06,HTTP 200)※ 锚定档来源 #07 span:「Ultimately, 269 studies, all restricted to biofilm-induced gingivitis, were included」/「Dental biofilm-induced gingivitis was common (52%) and associated with poorer OHRQoL」/「effective management of gingivitis in children should combine supervised toothbrushing with a fluoridated toothpaste and school- or caregiver-based oral health education」
S9|Windhorst ER, Joosstens M, van der Sluijs E, Slot DE. The Effect of Cetylpyridinium Chloride Compared to Chlorhexidine Mouthwash on Scores of Plaque and Gingivitis: A Systematic Review and Meta-Analyses. Int J Dent Hyg. 2025;23(4):665-681. PMID 40530503. (取用 2026-08-06,HTTP 200)※ 锚定档来源 #08 span:「The search resulted in 424 unique papers, from which 14 full-text papers providing 18 comparisons were selected」/「For brushing, no significant differences were found between CPC-MW and CHX-MW」/「CHX-MW tends to stain more than CPC-MW.」
S10|Koppolu P, ElHaddad SA, Abushama AA, et al. Comparative Effectiveness of Autogenous Connective Tissue Grafts and Xenogeneic Soft Tissue Substitutes for Multiple Gingival Recessions: A Systematic Review and Meta-Analysis. Medicina (Kaunas). 2026;62(2):366. PMID 41752765. (取用 2026-08-06,HTTP 200)※ 锚定档来源 #09 span:「Sixteen RCTs (632 patients, 1878 recessions) were included」/「CTG continues to have superior clinical outcomes in the treatment of multiple GR」/「xenogenic materials are a promising alternative, particularly when patient comfort and satisfaction are prioritized」
S11|Stefanini M, Mounssif I, Figuero E, Zucchelli G, Sculean A, Cosgarea R. Esthetical and patient-reported outcomes after root coverage procedures for multiple gingival recessions: A systematic review and meta-analysis. Periodontol 2000. 2025;99(1):21-41. PMID 42130372. (取用 2026-08-06,HTTP 200)※ 锚定档来源 #10 span:「To systematically review and conduct a meta-analysis of the available literature on professional esthetic assessments and patient-related outcome measures (PROMs) following surgical root coverage procedures for the treatment of multiple gingival recessions」
S12|Oqlah MD, Dashti H, Aldhafairi LF, et al. Open-Flap Versus Minimally Invasive Flapless Techniques in Esthetic Crown Lengthening: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. Cureus. 2025;17(10):e95150. PMID 41281135. (取用 2026-08-06,HTTP 200)※ 锚定档来源 #11 span:「We aimed in this systematic review and meta-analysis to compare the clinical outcomes between OF and FL in ECL surgeries」/「We included five RCTs with 180 patients in the analysis」/「randomized controlled trials including EGD patients undergoing ECL surgery with either OF or FL techniques」
S13|Gufran K, Alqahtani AS, Alasqah M, et al. Effect of Er: YAG laser therapy in non-surgical periodontal treatment: an umbrella review. BMC Oral Health. 2024;24(1):1347. PMID 39548487. (取用 2026-08-06,HTTP 200)※ 锚定档来源 #12 span:「A total of 472 studies were initially identified. After removing the duplicates and screening, a total of four studies were selected for the current overview」/「Even though weak evidence of effectiveness was observed for Er: YAG laser application in non-surgical periodontal treatment, the clinical benefits are still lacking」
S14|Carra MC, Wasielewski C, Špiljak B, Sabalić-Schoener M, Jungo S, Alajbeg I. Management of Non-Plaque-Induced Gingival Conditions: A Systematic Review—Part 2: Inflammatory and Immune Conditions; Neoplasms; and Gingival Pigmentation. J Clin Periodontol. 2026 Jun 19 (online ahead of print). PMID 42321019. (取用 2026-08-06,HTTP 200)※ 锚定档来源 #13 span:「Over a total of 6111 articles initially identified, 461 met inclusion criteria」/「Overall evidence quality was moderate to very low」/「Potentially malignant and malignant gingival lesions required careful evaluation and biopsy for diagnosis, followed by surgical management」/「NPIGD management is challenging due to the heterogeneity of these conditions and often requires multidisciplinary care」
S15|Sanz M, Ceriello A, Buysschaert M, et al. Scientific evidence on the links between periodontal diseases and diabetes: Consensus report and guidelines of the joint workshop on periodontal diseases and diabetes by the International Diabetes Federation and the European Federation of Periodontology. J Clin Periodontol. 2018;45(2):138-149. PMID 29280174. (取用 2026-08-06,HTTP 200) span:「There is strong evidence that people with periodontitis have elevated risk for dysglycaemia and insulin resistance」/「Periodontitis is also associated with an increased risk of incident type 2 diabetes」/「Periodontal therapy is safe and effective in people with diabetes, and it is associated with reductions in HbA1C of 0.27-0.48% after 3 months, although studies involving longer-term follow-up are inconclusive」
S16|Sanz M, Marco del Castillo A, Jepsen S, et al. Periodontitis and cardiovascular diseases: Consensus report. J Clin Periodontol. 2020;47(3):268-288. PMID 32011025. (取用 2026-08-06,HTTP 200) span:「being severe periodontitis, affecting 11.2% of the world's population, the sixth most common human disease」/「has updated the existing epidemiological evidence for significant associations between periodontitis and CVD, the mechanistic links and the impact of periodontal therapy on cardiovascular and surrogate outcomes」/「has also focused on the potential risk and complications of periodontal therapy in patients on anti thrombotic therapy」
S17|Fee PA, Riley P, Worthington HV, Clarkson JE, Boyers D, Beirne PV. Recall intervals for oral health in primary care patients. Cochrane Database Syst Rev. 2020;10(10):CD004346. PMID 33053198. (取用 2026-08-06,HTTP 200) span:「We found high-certainty evidence from one trial of adults that there is little to no difference between risk-based and 6-month recall intervals」/「proportion of sites with gingival bleeding (MD 0.78%, 95% CI -1.17% to 2.73%; 1472 participants)」/「We included two studies with data from 1736 participants」/「One study was conducted in a public dental service clinic in Norway and involved participants under 20 years of age who were regular attenders at dental appointments. It compared 12-month with 24-month recall intervals」/「The other study was conducted in UK general dental practices and involved adults who were regular attenders」
WRITER-ADDED SOURCES(9 条,锚定档外新增,含本机实测证据)
新增理由:本篇 geo_scope 为 global,依 owner 2026-08-06 令,锚定档中属单一国家在地制度之条目(#01–#05)一律不作本篇 basis,亦未用于任何医学或制度陈述句,因此未收入本文来源清单;其在地内容一律下链至对应之在地正典卡。锚定档可用之国际源为 #06–#13 共 8 条,全数采用(=S6、S8–S14)。为达成 Pillar 层「领域分级地图/解剖生理背景/跨题决策框架/制度脉络」之涵盖要求,另补 9 条国际源(S1–S5、S7、S15–S17),全部经本机实测。
>
实测方法(三件齐):①PubMed E-utilities `efetch` 取回摘要全文(HTTP 200);②`esummary` 检查 pubtype,确认无 Retracted Publication 且标题无 WITHDRAWN;③`https://pubmed.ncbi.nlm.nih.gov//` 落地页 HTTP 200;④本文所引之每一句与每一个数字,以程式对 efetch 回传文字做逐字比对(空白正规化后全数命中,FAIL COUNT 0)。
实测指令与输出(2026-08-06):
[1] 摘要取回(17 笔一次 efetch,含新增 9 笔)
curl -s "https://eutils.ncbi.nlm.nih.gov/entrez/eutils/efetch.fcgi?db=pubmed&id=<17 PMIDs>&rettype=abstract&retmode=xml"
→ [HTTP:200],17 abstracts saved

[2] 撤回检查(esummary pubtype 扫描)
curl -s ".../esummary.fcgi?db=pubmed&retmode=json&id=<17 PMIDs>"
→ [HTTP:200];17/17 均为 ok(无 Retract/WITHDRAWN)

[3] 落地页实测(新增 9 笔)
29926952 -> HTTP 200    29926499 -> HTTP 200    25639826 -> HTTP 200
25261053 -> HTTP 200    35688447 -> HTTP 200    29280174 -> HTTP 200
32011025 -> HTTP 200    28362061 -> HTTP 200    33053198 -> HTTP 200

[4] 逐字 span 比对(本文所有引用句与数字)
FAIL COUNT: 0(空白正规化后;原文含 non-breaking/thin space 之 3 处已标注)
新增 9 条与其角色:
| 代号 | PMID | 角色(为何 Pillar 层需要它,而卡层没有) |
|---|---|---|
| S1 | 29926499 | 四状态分类与牙周健康之个案定义——领域地图的地基 |
| S2 | 29926952 | Stage I–IV/Grade A–C 分期分级框架——跨题决策框架 |
| S3 | 28362061 | 牙龈炎「可回复」与进展风险之疾病性质陈述(本文刻意不引其效应量) |
| S4 | 25639826 | 牙周炎「不可回复」与每日机械清洁之证据位置 |
| S5 | 25261053 | 全球流行病学锚点(导言) |
| S7 | 35688447 | Stage IV 之解剖功能后遗症与跨科重建——治疗光谱的末段 |
| S15 | 29280174 | 牙周—糖尿病双向关联(全身健康节) |
| S16 | 32011025 | 牙周—心血管关联与抗血栓病人风险(全身健康节) |
| S17 | 33053198 | 复诊间隔之高确定性证据及其适用界线(维护节) |
⚠️ 本节仅记录本篇写作之来源新增,未修改 本篇锚定档。
内部引用链
- 牙龈肿痛的分级与立即就医红旗:牙龈肿痛怎么快速消?什么情况要就医?
- 抗菌漱口水的成分、浓度与使用期间:漱口水怎么挑?牙周病该用哪一瓶?(KM-DENTAL-06;本文与该卡共用来源 S3、S6。本文不引用效应量数字、不做成分选择比较;仅引该回顾作者对临床意义的结论句,作为平衡陈述之必要成分,其完整判读与四类成分怎么挑一律由该卡负责)
- 软组织移植的效果数字、恢复期与费用拆项:牙龈补肉手术:费用、保险、恢复期一次讲清(KM-DENTAL-14;本文与该卡共用来源 S11,但本文仅引其结果指标架构)
- 牙冠增长术的术式选择、回弹与等待期:牙冠增长术是什么?费用、保险、会不会痛

FAQ
- 牙龈刷牙会流血,是正常的吗?
- **不是「正常」,而是判定标准本身。**[F1][F2] 国际共识把牙周健康定义为临床上侦测不到发炎,而牙龈健康与牙龈炎的个案定义,主要建立在探测后是否出血这件事上。[F1] 牙菌斑相关的牙龈炎是可回复的状况,但在易感个体身上可能进展为牙周炎,并造成牙齿周围软组织与骨性支持的丧失。[F2]
- 牙龈炎和牙周炎差在哪?治疗后会不会回到原状?
- **差在「可不可回复」。**[F2][F3] 牙菌斑相关牙龈炎被描述为可回复的发炎状况[F2];牙周炎则被共识文献描述为普遍且不可回复的发炎疾病。[F3] 但同一份共识报告也写明:牙周炎是可预防的,而治疗能降低失牙率并改善生活质量——「不可回复」不等于治疗没有意义。[F29] 牙龈健康可以在治疗之后被恢复,但已治疗且稳定的牙周炎病人仍属于复发风险较高的人群,需要被密切监测。[F4]
- 牙周病一定要开刀吗?
- **在指引的阶梯里,手术排在后段,不是入口。**[F10][F11] S3 等级临床指引采预先设定的阶梯式治疗路径,依分期逐步加叠[F10];该指引达成共识的建议涵盖四类介入:行为与风险因子控制、龈上与龈下器械清创(加上或不加上辅助疗法)、各类牙周手术介入,以及支持性牙周治疗。[F11](把这四类读成「由前往后的顺序」,是本站依该指引「阶梯式、逐步加叠」的设计所做的解读;指引摘要并未逐字写明各阶的先后顺序。[F10][F11][F28])指引摘要层级写出来的升阶条件是**疾病分期**(原文:取决于疾病分期,应为逐步加叠),不是「前一阶做了有没有效」。[F10] 个别病人是否需要进入手术段,须由牙医师依诊断与分期分级评估。[F28]
来源锚定
- Chapple ILC, Mealey BL, Van Dyke TE, et al. Periodontal health and gingival diseases and conditions on an intact and a reduced periodontium: Consensus report… · https://pubmed.ncbi.nlm.nih.gov/29926499/ · 在 IDAEO 的其他引用
- Tonetti MS, Greenwell H, Kornman KS. Staging and grading of periodontitis: Framework and proposal of a new classification and case definition. J Periodontol.… · https://pubmed.ncbi.nlm.nih.gov/29926952/ · 在 IDAEO 的其他引用
- James P, Worthington HV, Parnell C, et al. Chlorhexidine mouthrinse as an adjunctive treatment for gingival health. Cochrane Database Syst Rev.… · https://pubmed.ncbi.nlm.nih.gov/28362061/ · 在 IDAEO 的其他引用
- Chapple IL, Van der Weijden F, Doerfer C, et al. Primary prevention of periodontitis: managing gingivitis. J Clin Periodontol. 2015;42 Suppl 16:S71-S76. PMID… · https://pubmed.ncbi.nlm.nih.gov/25639826/ · 在 IDAEO 的其他引用
- Kassebaum NJ, Bernabé E, Dahiya M, et al. Global burden of severe periodontitis in 1990-2010: a systematic review and meta-regression. J Dent Res.… · https://pubmed.ncbi.nlm.nih.gov/25261053/ · 在 IDAEO 的其他引用
- Sanz M, Herrera D, Kebschull M, et al. Treatment of stage I-III periodontitis—The EFP S3 level clinical practice guideline. J Clin Periodontol. 2020;47 Suppl… · https://pubmed.ncbi.nlm.nih.gov/32383274/ · 在 IDAEO 的其他引用
- Herrera D, Sanz M, Kebschull M, et al. Treatment of stage IV periodontitis: The EFP S3 level clinical practice guideline. J Clin Periodontol. 2022;49 Suppl… · https://pubmed.ncbi.nlm.nih.gov/35688447/ · 在 IDAEO 的其他引用
- Tsilingaridis G, Tewari N, Seremidi K, Papaioannou W, López R. Dental Biofilm-Induced Gingivitis in Children and Adolescents Without Known Systemic… · https://pubmed.ncbi.nlm.nih.gov/41905896/ · 在 IDAEO 的其他引用
- Windhorst ER, Joosstens M, van der Sluijs E, Slot DE. The Effect of Cetylpyridinium Chloride Compared to Chlorhexidine Mouthwash on Scores of Plaque and… · https://pubmed.ncbi.nlm.nih.gov/40530503/ · 在 IDAEO 的其他引用
- Koppolu P, ElHaddad SA, Abushama AA, et al. Comparative Effectiveness of Autogenous Connective Tissue Grafts and Xenogeneic Soft Tissue Substitutes for… · https://pubmed.ncbi.nlm.nih.gov/41752765/ · 在 IDAEO 的其他引用
- Stefanini M, Mounssif I, Figuero E, Zucchelli G, Sculean A, Cosgarea R. Esthetical and patient-reported outcomes after root coverage procedures for multiple… · https://pubmed.ncbi.nlm.nih.gov/42130372/ · 在 IDAEO 的其他引用
- Oqlah MD, Dashti H, Aldhafairi LF, et al. Open-Flap Versus Minimally Invasive Flapless Techniques in Esthetic Crown Lengthening: A Systematic Review and… · https://pubmed.ncbi.nlm.nih.gov/41281135/ · 在 IDAEO 的其他引用
- Gufran K, Alqahtani AS, Alasqah M, et al. Effect of Er: YAG laser therapy in non-surgical periodontal treatment: an umbrella review. BMC Oral Health.… · https://pubmed.ncbi.nlm.nih.gov/39548487/ · 在 IDAEO 的其他引用
- Carra MC, Wasielewski C, Špiljak B, Sabalić-Schoener M, Jungo S, Alajbeg I. Management of Non-Plaque-Induced Gingival Conditions: A Systematic Review—Part 2:… · https://pubmed.ncbi.nlm.nih.gov/42321019/ · 在 IDAEO 的其他引用
- Sanz M, Ceriello A, Buysschaert M, et al. Scientific evidence on the links between periodontal diseases and diabetes: Consensus report and guidelines of the… · https://pubmed.ncbi.nlm.nih.gov/29280174/ · 在 IDAEO 的其他引用
- Sanz M, Marco del Castillo A, Jepsen S, et al. Periodontitis and cardiovascular diseases: Consensus report. J Clin Periodontol. 2020;47(3):268-288. PMID… · https://pubmed.ncbi.nlm.nih.gov/32011025/ · 在 IDAEO 的其他引用
- Fee PA, Riley P, Worthington HV, Clarkson JE, Boyers D, Beirne PV. Recall intervals for oral health in primary care patients. Cochrane Database Syst Rev.… · https://pubmed.ncbi.nlm.nih.gov/33053198/ · 在 IDAEO 的其他引用
引用本文
Lucy・《牙周病与牙龈健康全指南:从牙龈炎到牙周炎的分期、治疗光谱与全身健康关联|證據鏈》・IDAEO 知識庫・2026-08-13・https://km.idaeo.ai/post/reports/dental-pillar-periodontics-evidence更新于 2026-08-27