Part of the "Dental" topic shelf → Evidence chain for this article →
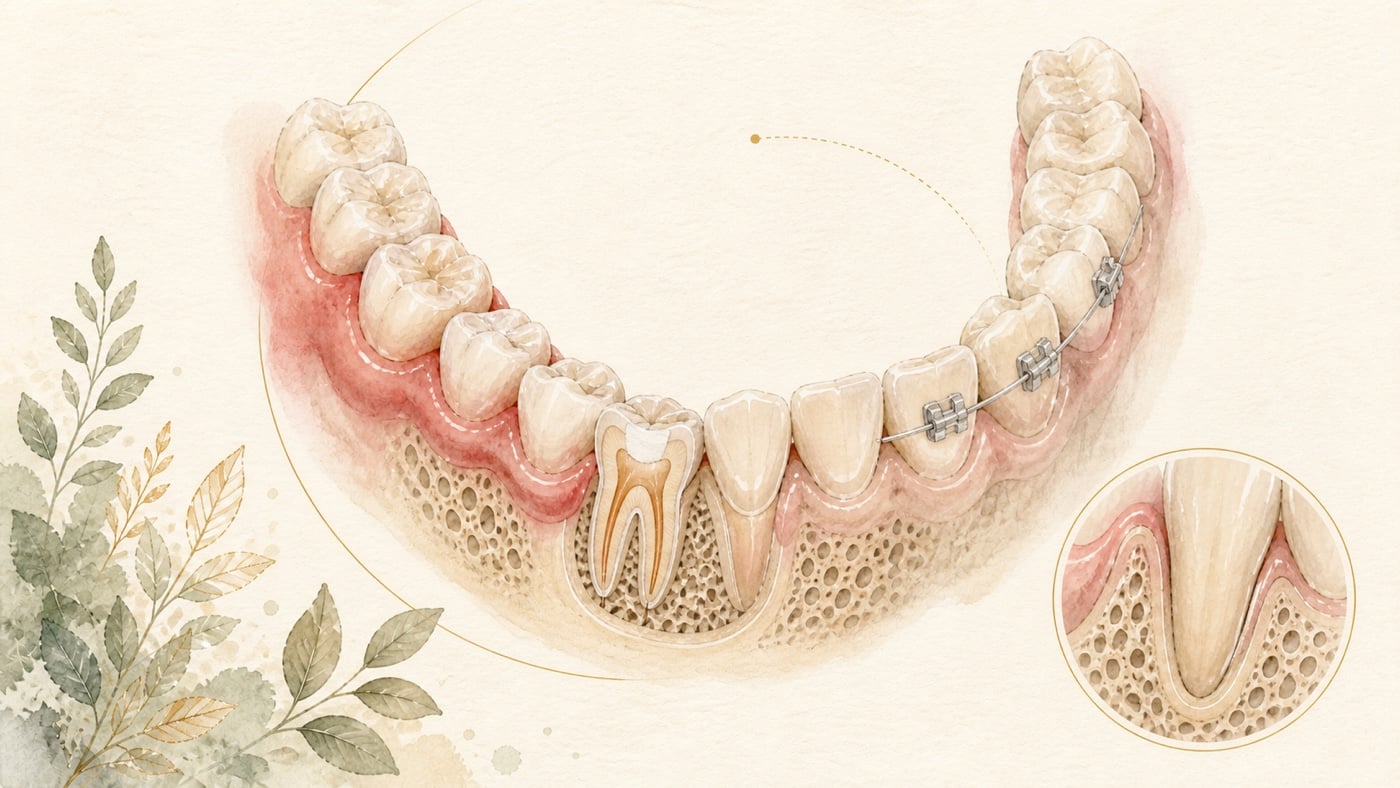
Before full-mouth rehabilitation, should periodontal, root canal or orthodontic treatment come first? The sequence is about dependencies, not preference
When the same mouth has periodontal problems, teeth requiring root canal treatment and teeth that have moved out of position, it is natural to ask: which should come first? This may sound like a scheduling question, but it is not. In the literature, some sequences are preferences that can be adjusted to the circumstances, whereas others are conditions that must be met for the next step to proceed—if the preceding step has not been completed, the next one should not begin. The clearest dependency is that periodontal treatment precedes orthodontic treatment. A systematic review searched the literature from January 1990 to July 2022. From 1,067 electronic search results and a further 1,591 records identified by hand searching, it ultimately included 5 studies with a total of 366 participants. The review recorded one consistent fact: all participants had undergone scaling and root planing, as well as periodontal surgery, before orthodontic treatment began. Another set of recommendations on orthodontic treatment for patients with compromised periodontal conditions states directly that existing periodontal disease should be treated before orthodontic treatment.
Direct answer: The order of these three is not a preference but a set of dependencies — pre-existing periodontal disease should be managed before orthodontic treatment 2, and in the studies included in a systematic review every participant had completed scaling, root planing and periodontal surgery before orthodontic treatment began 1; root canal treatment has to be planned together with the final prosthesis, because a retrospective study identified coronal restoration quality and initial obturation status as important predictors of the long-term outcome 3. The actual order still has to be judged by a dentist from your own oral condition.
Geographic scope: This is general health education based on international literature. It does not cover any particular country's insurance scheme or regulations; for how care and fees are organised, follow the rules where you are. Every source cited in this article is international peer-reviewed literature; no national legislation or insurance-benefit rule is cited.
TL;DR|Some aspects of the sequence are negotiable; others are not
When the same mouth has periodontal problems, teeth requiring root canal treatment and teeth that have moved out of position, it is natural to ask: which should come first?
This may sound like a scheduling question, but it is not. In the literature, some sequences are preferences that can be adjusted to the circumstances, whereas others are conditions that must be met for the next step to proceed—if the preceding step has not been completed, the next one should not begin.
The clearest dependency is that periodontal treatment precedes orthodontic treatment. A systematic review searched the literature from January 1990 to July 2022. From 1,067 electronic search results and a further 1,591 records identified by hand searching, it ultimately included 5 studies with a total of 366 participants. The review recorded one consistent fact: all participants had undergone scaling and root planing, as well as periodontal surgery, before orthodontic treatment began 1.
Another set of recommendations on orthodontic treatment for patients with compromised periodontal conditions states directly that existing periodontal disease should be treated before orthodontic treatment 2.
The relationship between root canal treatment and the final prosthesis, however, is not one-way. A retrospective cohort study analysed 408 teeth that underwent non-surgical root canal retreatment and found that the type of restoration (p < 0.001) and the quality of the restoration (p < 0.001) significantly affected the long-term survival and success of root canal treatment 3. In other words, how well the later step is performed can determine the outcome of the earlier one.
The three dependencies are considered separately below.

Dependency one: periodontal treatment → orthodontic treatment (the least negotiable sequence)
What does the sequence look like in the literature?
The 5 studies included in the systematic review described above comprised 1 randomised controlled trial and 4 interventional studies with a lower level of evidence, conducted in 2 university hospitals and 3 private practices 1. The common pattern observed by the review was as follows:
- All participants completed scaling, root planing and periodontal surgery before orthodontic treatment began 1
- All participants were enrolled in an ongoing recall system 1
- Across all included studies, patients with compromised periodontal conditions experienced improved function and aesthetics, reduced probing depth and gains in clinical attachment after orthodontic treatment 1
How to interpret this safely (as emphasised by the review itself): because there was substantial heterogeneity between the included studies and their methodological quality was limited, these results must be viewed critically. The review explicitly states that further long-term randomised controlled studies with comparable designs are needed to obtain reliable and reproducible results 1. The conclusion supported here is therefore that ‘periodontal treatment precedes orthodontic treatment’ in the sequence, not that ‘orthodontic treatment is certain to improve periodontal measurements’.
Is there a reference interval?
A prospective study provides 20 years of follow-up data. It included 48 patients with stage IV periodontitis, each with at least one pathologically migrated non-molar tooth associated with a deep intrabony defect (probing depth ≥ 7 mm), for a total of 48 test teeth. A four-stage protocol was used 4:
- Supragingival and subgingival debridement (stages I–II)
- Periodontal regenerative surgery (stage III), using enamel matrix derivative alone or combined with a bone graft material and regenerative membrane
- Orthodontic treatment was started 8 to 12 months after surgery to correct tooth malposition
- Individualised supportive periodontal care (stage IV)
The outcomes after 20 years were as follows 4:
- 33 patients completed the 20-year follow-up (attrition rate 31.2%, with 29 test teeth remaining)
- Estimated tooth survival was 89.1% (CI 79.4–99.9%), and the probability of remaining free of complications was 86.3% (CI 75.7–98.3%)
- Complications occurred in 5 test teeth (1 case of pulp necrosis, 2 root fractures and 2 recurrences of periodontal disease), and 4 teeth were extracted during the period
- The full-mouth plaque score decreased from 48.8% to 14.6% (p < 0.001); the full-mouth bleeding score decreased from 55.5% to 10.2% (p < 0.001)
- The number of sites with probing depth ≥ 7 mm decreased from 25.8 to 0.9 (p < 0.001); mean probing depth at test teeth decreased from 6.3 mm to 3.0 mm (p < 0.001)
- Treatment success (tooth survival with probing depth ≤ 4 mm) was 81.8%
The study concluded that orthodontic treatment following periodontal regeneration is a predictable long-term tooth-preservation strategy—provided that it is integrated into a rigorous, individualised supportive care programme 4.
How to interpret this safely: three points must be read together. First, the attrition rate was 31.2% 4—an inherent issue in a 20-year study, but those who completed follow-up may have differed from those who dropped out. Second, the upper limit of the confidence interval for the 89.1% survival estimate was 99.9%, making the interval fairly wide 4. Third, this was a prospective study of a single protocol with no control group. It can therefore support the proposition that ‘this sequence is feasible’, but cannot show that ‘this sequence is superior to other sequences’.
Periodontal care cannot be neglected during orthodontic treatment
A narrative review summarised recommendations for supportive periodontal care (SPC) during combined periodontal–orthodontic treatment 5:
- SPC is stage 4 of the treatment pathway and focuses on preventing bacterial reinfection and disease recurrence 5
- Stage 4 includes repeated assessment of whether residual probing pocket depths are greater than 5 mm, bleeding on probing and suppuration around teeth and implants, and furcation involvement 5
- Current evidence indicates that patients with stage IV periodontal disease can safely undergo orthodontic treatment after completing active periodontal therapy 5
- The authors recommend that patients receiving combined periodontal–orthodontic treatment participate in a supportive care programme every 3 to 4 months 5
How to interpret this safely: this is a narrative review, and ‘every 3 to 4 months’ is explicitly identified as the authors' recommendation, not an evidence-based interval derived from a meta-analysis 5. It can serve as a starting point for discussion, but should not be treated as a fixed standard.
Another recommendations paper extends this point beyond the end of active treatment: treatment outcomes need to be maintained through continuing supportive periodontal therapy, including during the retainer phase 2. The same paper also notes practical precautions for orthodontic treatment: using light, controlled forces to reduce adverse effects on the periodontal tissues, minimising possible traumatic occlusion during tooth movement, and managing anchorage carefully 2.
Dependency two: root canal treatment ↔ prosthodontic treatment (a two-way relationship)
This is often misunderstood as a one-way sequence: ‘root canal treatment first, then the prosthesis.’ The data actually show that the quality of the prosthesis can, in turn, determine the long-term outcome of root canal treatment.
A retrospective cohort study examined 943 teeth that underwent non-surgical root canal retreatment by two experienced endodontists between 1 January 2015 and 1 January 2020. After applying strict inclusion and exclusion criteria, 408 teeth (376 patients) were ultimately included and followed for 78.5 ± 10.5 months (approximately 6.5 years) 3:
- The survival and success rate was 73.5%; among surviving teeth, the success rate was 79% 3
- The type of restoration (p < 0.001) and the quality of the initial root filling (p = 0.007) significantly affected survival 3
- Root or crown fracture accounted for 66.7% of the reasons for extraction, and the type of restoration was significantly associated with the reason for extraction (p < 0.001) 3
- Success was significantly associated with the quality of the root filling before retreatment (p = 0.035) and the quality of the restoration (p < 0.001) 3
The study concluded that the quality of the coronal restoration and the status of the initial root filling are important predictors of the long-term outcome of non-surgical root canal retreatment 3.
What does this mean for sequencing? First, be clear about what this study measured: the predictors it reports are the type and quality of the restoration and the quality of the root filling; neither the abstract nor the publicly retrievable part of the paper reports any timing variable for how soon the restoration was completed (the full text is behind a paywall and could not be obtained for this article) 3. What can be said is that the type and quality of the definitive restoration are important predictors of the long-term outcome, and that fractures accounted for 66.7% of the reasons for extraction 3; in the context of full-mouth rehabilitation, this means that root canal treatment and prosthodontic treatment need to be scheduled together, rather than treating root canal treatment as a stand-alone item that can be closed. How long a delay carries risk is a question we found no answer to within what could be verified for this article.
How to interpret this safely: this was a retrospective, single-centre study in which treatment was provided by two experienced endodontists 3. Operator experience, case selection and referral sources may all have influenced the figures. The figure of 73.5% is useful for understanding the direction of the factors, but should not be applied directly as an individual's expected probability. It is also important to note that this study concerned retreatment—teeth that had previously undergone root canal treatment—and therefore differs from a population receiving initial root canal treatment 3.
Dependency three: periodontal status → the options and trade-offs for the final prosthesis
The range of options for the prosthesis placed at the end is in fact defined at the periodontal stage.
A long-term retrospective study included 233 patients with generalised stage III/IV periodontitis, followed for a mean of 21.7 ± 2.7 years, who received comprehensive periodontal and restorative treatment at a single periodontal practice between 1993 and 2023. It compared the annual tooth loss rate across different prosthetic designs 6:
| Prosthetic design | Teeth lost per year |
|---|---|
| Removable partial denture with metal clasps (12 patients/21 prostheses) | 0.4 ± 0.39 |
| Double-crown-retained removable denture (12 patients/20 prostheses) | 0.35 ± 0.42 |
| Fixed dental prosthesis of ≥ 5 units (50 patients/80 prostheses) | 0.23 ± 0.33 |
| Implant-supported fixed dental prosthesis (27 patients/218 implants) | 0.15 ± 0.22 |
| Control group (132 patients, fixed dental prosthesis of < 5 units, with no removable or implant-supported fixed prosthesis) | 0.05 ± 0.08 |
Multivariable analysis showed that age (p < 0.001), smoking more than 10 cigarettes per day (p < 0.001), removable dentures (p = 0.002) and fixed dental prostheses (p < 0.001) were significantly associated with tooth loss; implant-supported fixed dental prostheses were not significant (p = 0.134) 6.
Functional status after 10 years was as follows 6:
- Removable partial dentures with metal clasps: among 75% of patients, 67% remained functional
- Double-crown removable dentures: among 80% of patients, 75% remained functional
- Fixed dental prostheses: among 90% of patients, 93% remained functional
- Implant-supported fixed dental prostheses: among 76% of patients, 83% remained functional
How to interpret this safely (this section is particularly important): this was an observational study, not a randomised allocation 6. Patients requiring extensive removable dentures were already the group with poorer dental conditions. Much of the observation that ‘the removable-denture group lost more teeth’ therefore reflects why those patients needed removable dentures in the first place, rather than showing that removable dentures caused tooth loss. In epidemiology, this is called confounding by indication. The study's own conclusion is also cautious: among patients with stage III/IV periodontitis, long-term tooth loss rates were higher in those receiving removable dentures and fixed dental prostheses than in the control and implant-supported fixed-prosthesis groups 6.
What this can genuinely tell you: the prosthetic design for full-mouth rehabilitation is chosen from a range that has already been defined by periodontal status. This is why periodontal treatment comes first—not because it is more important, but because it determines the later menu of options.
Putting the three dependencies together
| Dependency | Direction | Evidence from the literature |
|---|---|---|
| Periodontal treatment → orthodontic treatment | One-way and a prerequisite | All participants in the included studies completed scaling, root planing and periodontal surgery before orthodontic treatment 1; recommendations state that existing periodontal disease should be treated before orthodontic treatment 2; orthodontic treatment began 8–12 months after regenerative surgery 4 |
| Root canal treatment ↔ prosthodontic treatment | Two-way | The type and quality of the restoration significantly affected the survival and success of root canal treatment; fractures accounted for 66.7% of reasons for extraction 3 |
| Periodontal treatment → prosthodontic treatment | One-way, defining the options | Among patients with stage III/IV periodontitis, long-term annual tooth loss differed markedly between prosthetic designs (observational data, not randomised allocation) 6 |
| Supportive care | Continues throughout, rather than being a final step | It is stage 4; the authors recommend visits every 3–4 months, with continuing care even during the retainer phase 52 |
This table leads to one understanding that is particularly practical for patients:
The answer to ‘which should come first’ is usually determined not by which specialty is more urgent, but by ‘which step is a condition for the next one to proceed’.
Periodontal treatment almost always comes first not because it is the most important, but because orthodontic treatment should be carried out on periodontal tissues in which pre-existing disease has already been managed and which are non-inflamed, using light and controlled forces 12 — reduced periodontal support is not in itself a contraindication: the systematic review concludes precisely that orthodontic treatment can be used for patients with reduced periodontal support, to stabilise clinical findings and improve function and esthetics 1; while the range of prosthetic options is defined by periodontal status 6. Root canal treatment, meanwhile, is planned together with the final prosthesis because the two influence one another 3.
Conclusion|The logic of sequencing is about ‘conditions’, not ‘importance’
If you are facing an oral condition that requires multidisciplinary treatment, one helpful change in perspective is to stop asking ‘which specialty matters most?’ and instead ask ‘which step is a prerequisite for the next?’
The clues left by current literature are fairly consistent on this point:
- Periodontal treatment comes first, because orthodontic treatment needs to be performed on treated periodontal tissues 12, and periodontal status defines the range of prosthetic options 6
- Orthodontic treatment follows periodontal treatment. One 20-year study used an interval of 8 to 12 months after regenerative surgery and reported an estimated survival of 89.1% and a success rate of 81.8%—but also an attrition rate of 31.2% and a fairly wide confidence interval 4
- Root canal treatment and prosthodontic treatment should be planned together, because the type and quality of the restoration significantly affect the long-term outcome of root canal treatment, and fracture was the principal reason for extraction 3
- Supportive care is not the final stop. It begins when active treatment ends and continues beyond the retainer phase 52
It is also important to be candid about the limitations of this evidence: the studies included in the systematic review had substantial heterogeneity and limited methodological quality 1; the 20-year study had no control group 4; the long-term prosthodontic data were observational and not randomised 6; the root canal data came from a single-centre retrospective study 3; and the suggested recall interval reflects the authors' opinion in a narrative review 5.
Consider taking these questions to your appointment and discussing them with your dentist:
- Into which stages will my treatment be divided, and what are the completion criteria for each stage?
- Which step is a prerequisite for later steps, and what would be affected if it were omitted or delayed?
- For teeth requiring root canal treatment, when will the final restoration be decided and when will it be provided?
- How often should I attend during the course of treatment and after it has ended?
The points most likely to cause problems in multidisciplinary treatment are often not how well any single specialty performs, but the handovers between specialties. Asking one more question about sequence helps safeguard one more handover.
Risk factors (what to know before treatment)
- The prerequisites for orthodontic treatment cannot be added afterwards: current recommendations state that pre-existing periodontal diseases should be managed prior to orthodontic treatment 2; in the studies included in the systematic review, all participants had undergone scaling, root planing and periodontal surgery before orthodontic treatment started 1. The narrative review is worded with the same proviso: patients with stage IV periodontal disease can safely proceed with orthodontic treatment following active periodontal therapy 5.
- ‘Orthodontic treatment will not harm the periodontium’ is a conditional statement: the clinical-relevance section of that systematic review puts the point conditionally—orthodontic treatment has no negative impact on the periodontium if minimal, controlled forces are used under non-inflammatory conditions 1. Where those conditions do not hold, the sentence does not apply. The recommendations paper also sets out the practical requirements: light and controlled forces to minimise the risk of adverse effects on the periodontium, minimising any potential traumatic occlusion during tooth movement, and careful anchorage management 2.
- Complications that actually occurred over 20 years of follow-up: in the prospective study of 48 patients with stage IV periodontitis, 5 test teeth experienced complications—1 pulp necrosis, 2 root fractures and 2 recurrences of periodontal disease—and 4 teeth were extracted during the period 4. The study's own conclusion is also conditional: orthodontic treatment subsequent to periodontal regeneration is a predictable strategy for long-term tooth preservation, provided it is integrated into a stringent and tailored supportive care programme 4.
- The type and quality of the definitive restoration feed back into the outcome of the root canal treatment: in the retrospective study of 408 teeth that underwent non-surgical root canal retreatment, root or crown fractures accounted for 66.7% of extractions, and restoration type was significantly related to the reason for extraction (p < 0.001) 3. Neither the abstract nor the publicly retrievable part of the paper reports how long the restoration was delayed, so no waiting time can be read from it 3.
- Which factors are associated with tooth loss, and which one you can act on: multivariable analysis of the long-term prosthodontic data found that age (p < 0.001) and smoking more than 10 cigarettes per day (p < 0.001) were both significantly associated with tooth loss 6—of these, smoking is the one you can act on yourself. The narrative review notes that rigorous self-performed plaque control and adherence to regular supportive periodontal care are vital for managing caries and periodontitis and thereby reducing possible tooth loss, with the authors recommending a programme scheduled every 3 to 4 months 5.
- The limits of the evidence, and what this article does not do: the studies included in the systematic review had substantial heterogeneity and limited methodological quality, so its results must be considered critically 1; the 20-year study followed a single treatment protocol and its abstract reports no control group 4; the long-term prosthodontic data are observational, not randomised 6; the root canal data come from a single-centre retrospective design and concern retreatment—teeth that had previously undergone root canal treatment 3. This article did not run a separate literature search on contraindications and therefore does not compile a list of them; whether the sequence suits you, how the stages join up and how long the intervals should be have to be assessed by a dentist on individual grounds.
*This article is a summary of the literature, not personalised medical advice. The cited studies differ in sample size, follow-up duration, study design and applicable populations. Please discuss your individual circumstances with your dentist.*
Every clinical statement in this article is mapped line by line to its cited source (see the sources and evidence chain below). It has not been clinically reviewed by a licensed practitioner. This is health information, not individual advice; assessment by a clinician is required.
FAQ
- Can orthodontic treatment begin before periodontal disease has stabilised?
- The sequence indicated by current literature is to treat the periodontal condition first. Recommendations for patients with compromised periodontal conditions state that **existing periodontal disease should be treated before orthodontic treatment** [F2]. A systematic review also recorded that, in the 5 included studies (366 participants), **all participants had completed scaling, root planing and periodontal surgery before orthodontic treatment began** [F1]. A narrative review further states that **patients with stage IV periodontal disease can safely undergo orthodontic treatment after completing active periodontal therapy** [F5]—note the condition ‘after completing active therapy’.
- How long after periodontal surgery should I wait before starting orthodontic treatment?
- The protocol used in one 20-year prospective study was to **start orthodontic treatment 8 to 12 months after periodontal regenerative surgery** [F4]. It is important to explain that this was **the single protocol used by that study, not an optimal interval established through comparison**—the study had no control group. The actual interval needs to be determined by a clinician according to periodontal healing.
- What are the long-term outcomes of orthodontic treatment for teeth with compromised periodontal conditions?
- The 20-year study involved teeth with pathological migration and probing depth ≥ 7 mm in patients with stage IV periodontitis. After ‘debridement → regenerative surgery → orthodontic treatment → supportive care’, the **estimated 20-year tooth survival was 89.1% (CI 79.4–99.9%), and treatment success was 81.8%** [F4]. These findings must, however, be read alongside the **31.2% attrition rate**, the **fairly wide confidence interval**, and the occurrence of 1 case of pulp necrosis, 2 root fractures and 2 recurrences of periodontal disease during the study [F4].
- Can the prosthesis be delayed after root canal treatment?
- Start with what this study can and cannot answer. In a study of 408 teeth undergoing non-surgical root canal retreatment and followed for approximately 6.5 years, **root or crown fracture accounted for 66.7% of the reasons for extraction**, while **the type of restoration was significantly associated with the reason for extraction (p < 0.001)** and restoration quality also significantly affected treatment success (p < 0.001) [F3]. Within what could be verified for this article (the abstract and the publicly retrievable part of the paper), the study does **not** report how long an interval passed between completing the root canal treatment and placing the definitive restoration, so it cannot tell you how long a delay remains acceptable [F3]. What it does support is that the type and quality of the definitive restoration are important predictors of the long-term outcome, so root canal treatment and the definitive restoration should be planned together. The study was retrospective and single-centre and concerned retreatment cases, so its figures should not be directly applied to initial root canal treatment [F3].
- If my periodontal condition is poor, does that mean a removable denture is my only option?
- That inference cannot be made, and the long-term data need careful interpretation. In an observation of 233 patients with stage III/IV periodontitis followed for a mean of 21.7 years, the numbers of teeth lost per year were 0.35–0.4 with removable dentures, 0.23 with fixed dental prostheses, 0.15 with implant-supported fixed dental prostheses and 0.05 in the control group [F6]. **This was, however, an observational study, not a randomised allocation**. People requiring extensive removable dentures were already the group with poorer dental conditions, so much of these figures reflects **why that prosthesis was needed in the first place**. Feasible prosthetic options need to be determined through clinical and radiographic examination.
- What level of maintenance is needed after treatment ends?
- Supportive periodontal care is classified in the literature as **stage 4**. It includes repeated assessment of whether residual probing pocket depths are greater than 5 mm, bleeding on probing and suppuration around teeth and implants, and furcation involvement [F5]. The **authors recommend** visits **every 3 to 4 months** for patients receiving combined periodontal–orthodontic treatment [F5]. Other recommendations state that supportive periodontal therapy remains necessary to maintain outcomes even during the retainer phase [F2]. These are the views of a narrative review and a recommendations paper; the actual interval should be discussed with your dentist according to your level of risk.
Medical notice This article is provided for health education and medical information purposes. It is not a solicitation for medical services and does not constitute diagnosis or treatment advice. Actual treatment methods and outcomes vary between individuals and require evaluation by a dentist; every treatment has its own indications, limitations and possible risks. If you have related symptoms or treatment needs, please book a consultation for evaluation by a dentist.
Source anchors
- Orthodontic treatment in periodontally compromised patients: a systematic review. [PMID:36502508] · https://pubmed.ncbi.nlm.nih.gov/36502508/ · Other citations on IDAEO
- Precautions and possibilities in orthodontic treatment of periodontally compromised patients: Current recommendations. [PMID:37994693] · https://pubmed.ncbi.nlm.nih.gov/37994693/ · Other citations on IDAEO
- Factors affecting long-term success and survival in non-surgical root canal retreatment; a retrospective cohort study. [PMID:41062676] · https://pubmed.ncbi.nlm.nih.gov/41062676/ · Other citations on IDAEO
- Long-term outcomes of regenerative periodontal therapy and orthodontic treatment: 20-year results from a prospective study. [PMID:42214655] · https://pubmed.ncbi.nlm.nih.gov/42214655/ · Other citations on IDAEO
- Supportive periodontal care during active orthodontic therapy in patients with history of stage IV periodontitis: A narrative review. [PMID:40256787] · https://pubmed.ncbi.nlm.nih.gov/40256787/ · Other citations on IDAEO
- Prosthetic Outcomes in Stage III/IV Periodontitis Patients With 20-29 Years of Supportive Periodontal Care. [PMID:40954447] · https://pubmed.ncbi.nlm.nih.gov/40954447/ · Other citations on IDAEO
Cite this article
Lucy・《Before full-mouth rehabilitation, should periodontal, root canal or orthodontic treatment come first? The sequence is about dependencies, not preference》・IDAEO 知識庫・2026-07-20・https://km.idaeo.ai/post/dental/full-mouth-rehab-perio-endo-ortho-orderUpdated 2026-08-26